
Tirzepatide before-and-after photographs can show that someone’s appearance changed. They cannot tell you which product and dose were used, how long treatment continued, whether the person had diabetes, or what happened after the photograph. Clinical trial results offer a more useful starting point, provided their numbers stay attached to the people and time periods actually studied.
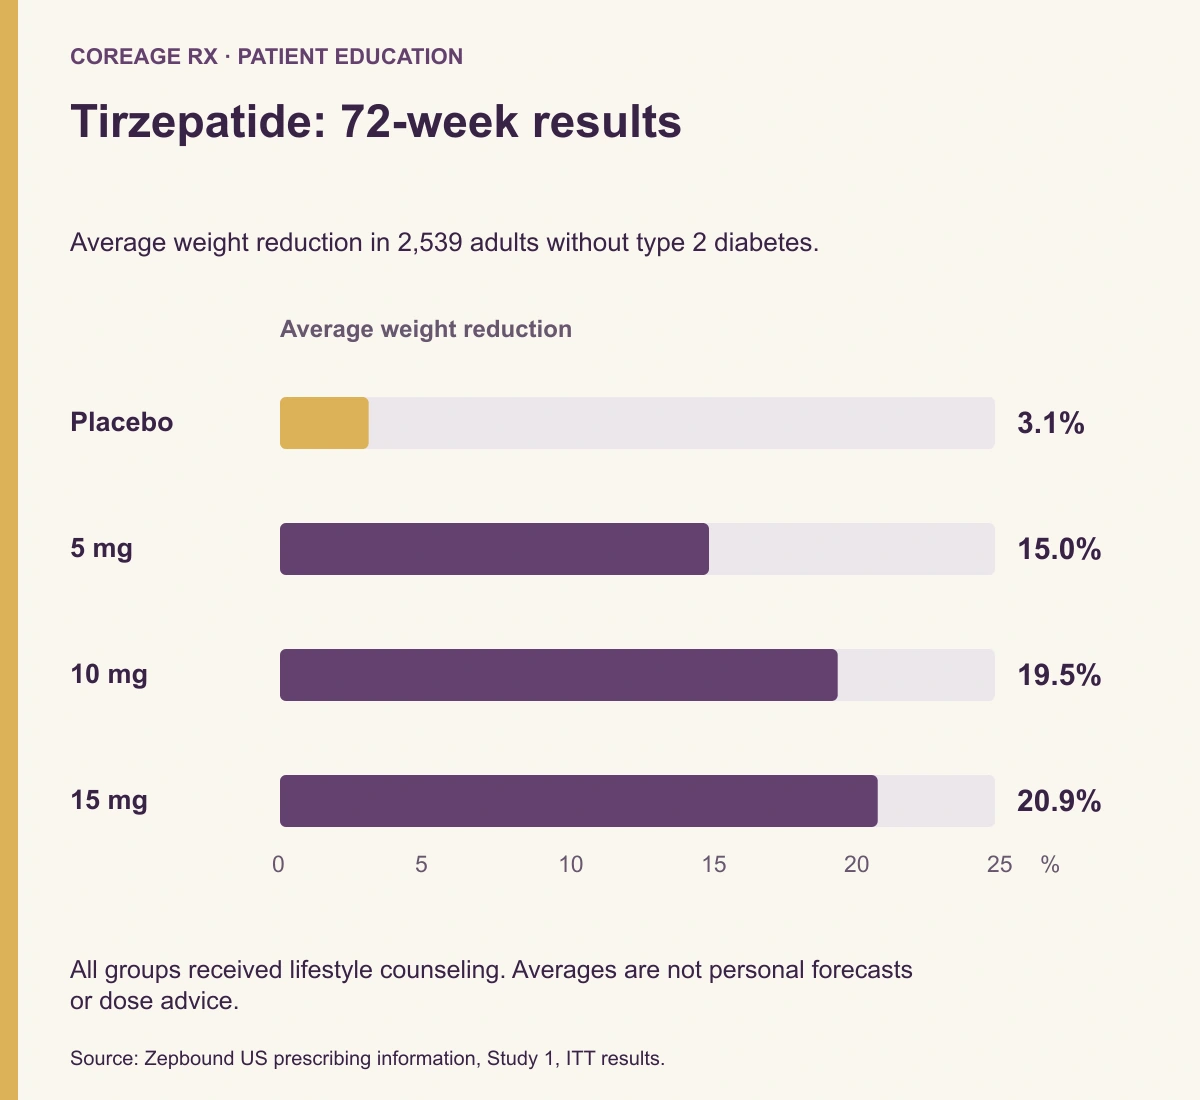
In a 72-week study of adults with obesity or qualifying overweight without type 2 diabetes, average weight reductions ranged from 15.0% to 20.9% across the studied tirzepatide doses, compared with 3.1% with placebo. Those are group averages during a structured program, not a six-month promise or a forecast for an individual. This guide explains what the evidence can tell you before treatment and what to track afterward.
Start by identifying the medicine and treatment goal
Tirzepatide is the active ingredient in both Zepbound and Mounjaro, but their approved uses differ. Zepbound is labeled for long-term weight management in specified adults and for moderate to severe obstructive sleep apnea in adults with obesity. Mounjaro is labeled for type 2 diabetes, including specified pediatric use, and cardiovascular risk reduction in adults with type 2 diabetes at high risk for those events.
That distinction matters when comparing results. A diabetes trial may focus primarily on blood glucose, while an obesity trial focuses on body-weight change. Participants can have different starting weights, other medicines, and health conditions. Read the Zepbound label and Mounjaro label for the exact uses and study populations.
A compounded preparation has another important distinction: it is not an FDA-approved Zepbound or Mounjaro product, and the branded trial results do not establish the effectiveness or quality of every compounded formulation. Our compounded GLP-1 guide explains those differences.
What the 72-week weight-management trials found
The Zepbound prescribing information reports two major trials with different populations. Both included reduced-calorie eating and physical-activity counseling, and both assessed weight change at 72 weeks after gradual dose escalation.
| Trial population | Studied weekly dose | Average weight reduction at week 72 |
|---|---|---|
| Without type 2 diabetes | Placebo | 3.1% |
| Without type 2 diabetes | 5 mg | 15.0% |
| Without type 2 diabetes | 10 mg | 19.5% |
| Without type 2 diabetes | 15 mg | 20.9% |
| With type 2 diabetes | Placebo | 3.2% |
| With type 2 diabetes | 10 mg | 12.8% |
| With type 2 diabetes | 15 mg | 14.7% |
The study without diabetes enrolled 2,539 adults. The study with diabetes enrolled 938 adults with a BMI of at least 27 and type 2 diabetes. These numbers come from the label’s intention-to-treat results, an analysis that accounts for the randomized groups rather than showing only selected success stories.
The table should not become a dose-shopping chart. A higher dose is not automatically the best choice for a particular person. Response, tolerability, indication, and the prescriber’s plan matter. The Zepbound dosage guide provides context for discussing a prescribed schedule.
How percentages translate into pounds
A percentage describes change relative to starting weight. Losing 15% of 200 pounds would equal 30 pounds; losing 15% of 300 pounds would equal 45 pounds. These are arithmetic examples, not expected outcomes for two hypothetical patients.
This is why a post saying “I lost 40 pounds” is incomplete without the starting weight and time frame. The same number of pounds can represent different proportional changes and different health circumstances.
Also check whether a reported percentage refers to starting weight, weight after an initial treatment period, or the difference from a comparison group. Those denominators are not interchangeable. A claim of “20% more weight loss” can describe a relative comparison rather than an additional twenty percentage points of body weight.
If you are comparing medicines, our tirzepatide versus semaglutide results guide keeps the study doses, populations, and comparison method together.
What to expect in the first month
The first month is a period of starting treatment, learning the device, and assessing tolerance. It is not a miniature version of a 72-week trial. Some people notice an appetite change early; others notice a less obvious change while their care plan is being established.
The Zepbound label starts with 2.5 mg weekly for four weeks before moving to 5 mg. The starting dose is not an approved maintenance dose. Later increases depend on the labeled schedule and clinical decisions about response and tolerance. Do not accelerate the plan to match a photograph or another person’s timeline.
Early scale readings can also be influenced by hydration and bowel patterns. A few measurements cannot separate every contributor to weight change. Track a trend using a consistent routine that does not become distressing, and discuss what frequency of weighing makes sense for you.
Our tirzepatide first-month guide covers the practical questions that arise before a long-term result can reasonably be assessed.

What about three-month or six-month results?
Long-term trial averages cannot be divided by the number of months to create a reliable monthly target. Dose escalation takes time, individual responses vary, and weight change is not necessarily linear.
For example, dividing a 72-week average in half does not establish the expected loss at 36 weeks. It also ignores people who interrupt treatment, change doses, or discontinue because of side effects or access problems.
A useful review asks what has happened at the dose you have actually been able to take, whether appetite and nutrition are manageable, and whether health markers are moving toward the agreed goals. It should also account for missed doses, changes in other medicines, and treatment costs.
If progress has slowed, our tirzepatide plateau guide offers questions to bring to the appointment. Adding extra doses or eating as little as possible is not an appropriate response to a slower month.
Results are more than an appearance change
Before treatment, decide with the clinician what improvement would be meaningful. Weight and waist measurements may be useful, but so may glucose control, blood pressure, daily mobility, sleep-apnea outcomes, or the ability to sustain a comfortable eating routine.
Do not assume every tirzepatide product has evidence or approval for every health outcome. A person using Zepbound for sleep apnea needs the appropriate sleep assessment and follow-up. Improvement on the scale does not independently prove that positive-airway-pressure treatment can be stopped. See our tirzepatide and sleep-apnea guide.
Strength and nutrition also deserve attention. Eating less does not automatically mean eating adequately. Report persistent vomiting, very low intake, fatigue, or difficulty maintaining ordinary activity. Our tirzepatide protein and muscle guide explains how to discuss food intake and resistance activity without adopting an extreme diet.
Why photographs are weak evidence
A photograph usually leaves out the denominator: how many people started the program, how many stopped, and how many had little change. Lighting, clothing, posture, camera distance, and the choice of which image to publish can alter what the comparison appears to show.
Even an authentic photograph does not isolate the medication’s contribution. The person may also have changed food intake, activity, another prescription, or a medical condition. Their experience can be meaningful without being a controlled estimate of treatment effect.
When evaluating a story, look for the treatment dates, exact product, relevant diagnosis, other changes, side effects, and disclosure of any paid relationship. Be cautious if the story offers a guaranteed timeline or implies that everyone should reach the same body shape.
The illustrations in this article are editorial visuals. They are not patient transformations, and no generated image is being presented as evidence of a treatment outcome.
What happens after treatment stops?
Maintenance deserves a discussion before the first prescription. In Zepbound’s randomized-withdrawal study, participants first received tirzepatide for 36 weeks. Of 783 starters, 670 reached randomization and were assigned either to continue tirzepatide or switch to placebo for another 52 weeks.
During that later period, the placebo group gained an average of 14.0% relative to its weight at week 36. The group continuing treatment lost another 5.5% relative to week-36 weight. These percentages are not measured from the original starting weight. The study also selected people who had reached the end of the initial treatment period, which limits how its results apply to everyone beginning treatment. See the withdrawal study in the Zepbound label.
The practical lesson is to plan ongoing care, access, and monitoring. It does not mean a person has failed if weight returns. Our stopping tirzepatide and maintenance guide explains the questions to address when treatment changes.

Safety belongs in every results discussion
Tirzepatide can cause nausea, diarrhea, vomiting, constipation, and other effects. Severe or persistent abdominal pain, significant dehydration, or allergic symptoms require prompt medical attention. It is contraindicated for people with a personal or family history of medullary thyroid carcinoma or MEN2, and other history and medicines require review.
Pregnancy plans and contraception also matter. Tirzepatide labeling advises people using oral hormonal contraceptives to switch to a nonoral method or add a barrier method for four weeks after starting and for four weeks after each dose increase. Our tirzepatide and birth-control guide explains the conversation.
Nausea is not proof of better results. Analyses of the SURMOUNT studies found substantial weight reductions among participants without nausea, vomiting, or diarrhea. Treatment should not require chasing side effects.
Questions to ask before you start
Ask which diagnosis is being treated, which exact product is proposed, how response will be assessed, and what happens if side effects or costs interrupt the plan. Ask who will answer questions between visits and how the clinician will decide whether to maintain, change, or stop treatment.
CoreAge Rx’s tirzepatide care information can help you prepare for that discussion. Pair it with the tirzepatide questions guide. A useful before-and-after record includes your health, tolerance, and ability to maintain care—not just two photographs.
Educational information for adults; individual treatment decisions require a qualified clinician. Sources checked September 27, 2026. Original AI-generated article illustrations depict fictional people and objects, not patient outcomes. Other editorial images are illustrative. Graphics summarize the cited sources.





